Abstract
A 4-year-old boy presented to our clinic with chronic-phase Chronic myeloid leukemia (CML), mild constitutional symptoms, and hepatosplenomegaly. He initiated imatinib and achieved Molecular response 4 (MR4) but experienced gastrointestinal intolerance requiring hospital admission, prompting a switch to dasatinib. He subsequently completed two years of dasatinib with good tolerance and sustained Molecular response 4 (MR4). Tyrosine kinase inhibitor (TKI) discontinuation was attempted at nine years of age, and the patient has maintained Molecular response 4 (MR4) for more than six years to date, demonstrating successful Treatment-free remission (TFR) and avoidance of Tyrosine kinase inhibitor-related growth impairment during puberty. He exhibited no withdrawal symptoms and continues to show normal growth. This case report adds to the limited evidence supporting the safety and feasibility of TKI discontinuation in the pediatric Chronic Myeloid Leukemia (CML) population.
Case Presentation
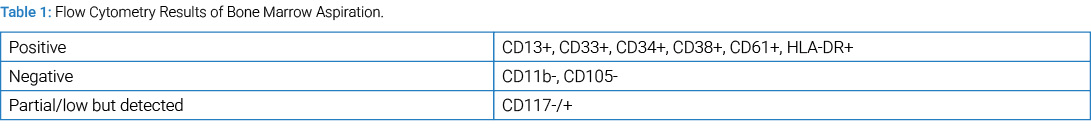
A previously healthy 4-year-old boy presented to a local practitioner with a history of rhinorrhoea and productive cough, pallor, anorexia, and asthenia. His mother also reported approximately 10% weight loss over the preceding couple of months. Other symptoms, such as pain, fever, hemorrhage, dyspnoea, skin, gastrointestinal or urinary alterations, were denied. The physical examination was unremarkable except for hepatosplenomegaly. Analytical studies revealed: haemoglobin: 8.3 g/dL, white blood count: 31,850/μL, absolute neutrophil count: 16.560/μL, absolute lymphocyte count: 4.780/μL, basophile count: 0/μL, metamyelocytes: 5.730/μL, myelocytes: 960/μL, blasts: 1910/μL (6%) and 356.000/μL platelets, normal uric acid, an elevated Lactate dehydrogenase (LDH) of 995 U/L and no other results of notice. An abdominal ultrasound was performed and revealed hepatomegaly (12.9 cm), splenomegaly (20.2 cm), and retroperitoneal lymphadenopathy. The patient’s medical history also noted that his maternal grandfather had Chronic myeloid leukemia (CML). The boy was subsequently transferred to our institution due to suspicion of acute leukemia. Physical examination revealed a 95-percentile height and 90-percentile weight child [1], paleness, hepatomegaly (3.5 cm below costal margin) and splenomegaly (until the left iliac crest margin), no palpable lymphadenopathy, no signs of neurological or testes involvement and no other abnormalities. Chest X-ray was normal. Flow cytometric analysis demonstrated 7.27% myeloid blasts in peripheral blood and 8% in bone marrow (summarized in Table 1).
Conventional cytogenetic analysis revealed t(9;22) in 20 metaphases, resulting in the BCR-ABL1 fusion gene characteristic of Chronic Myeloid Leukemia (CML). Bone marrow biopsy showed a hypocellular marrow with chronic myeloproliferative traits. BCR-ABL1 quantification International Scale (IS) in peripheral blood was 43,383. A diagnosis of chronic myeloid leukemia was established, and the patient initiated imatinib at 400 mg/m² in October 2011.
The patient achieved and sustained a Major Molecular response 4 (MR4), defined as a BCR-ABL1 transcript level ≤ 0.01% (IS). He completed nearly four years of imatinib therapy but experienced difficulties tolerating the treatment, including one hospital admission due to anorexia, vomiting, and inability to maintain oral intake. These episodes worsened in 2015, prompting our team to switch the Tyrosine kinase inhibitor (TKI) to dasatinib, which was well tolerated. The patient completed two years of dasatinib treatment and maintained MR4 throughout, with no clinical or laboratory complications and normal growth. Given the stability of his molecular response and the recognized long-term adverse effects of TKIs in pediatric patients such as growth impairment and endocrinopathies [2–5], we considered TKI discontinuation and an attempt at Treatment-Free Remission (TFR). To the best of our knowledge at that time, no open clinical trial was available for his enrolment. Before discontinuing TKI therapy, we clearly defined that treatment would be immediately resumed if loss of MR4 was documented. The legal guardian was fully informed about the experimental nature of this decision and provided written consent.
Dasatinib was discontinued in May 2017, when the patient was nearly 10-year-old. He was subsequently monitored monthly for six months and then every three months. During follow-up, he demonstrated normal growth (approximately at the 50th percentile for weight and the 95th percentile for height according to World Health Organization standards). He did not experience any symptoms suggestive of TKI withdrawal syndrome. Even though concern for potential neurocognitive impairment was not observed [6], the patient has shown normal development, performs well academically, and reports a satisfactory circle of friends. From the TKI stop to this date, more than six years have passed, and an MR4 response has been maintained throughout the entire follow-up.
We consider this a successful case of treatment-free remission of CML, which shall add to the previous report of Shima et al. [7] on the feasibility of TKI discontinuation in the pediatric population. We report the experience of dasatinib discontinuation that spared a child of all the possible TKI secondary effects during puberty, and, like the previous report, did not find any withdrawal syndrome—a report by Millot et al. [8] retrospectively selected pediatric patients with imatinib discontinuation (switching to another TKI was deemed an exclusion criterion) and reported no impact on outcomes in the pediatric age group; this study also failed to identify patients with withdrawal syndrome [8]. It is also important to emphasize that even in adult CML, the earliest attempts at TFR were undertaken in an experimental context, without guideline support, and were initially met with patient hesitancy [9].
We await the results of the ongoing trial NCT03817398 [10], a phase II study evaluating the effects of discontinuation of tyrosine kinase inhibitors on treatment-free remission in children, adolescents, and young adults with chronic-phase chronic myeloid leukemia. The trial began in November 2019 and is expected to be completed in June 2026. Our case report, together with previously published retrospective analyses [11], may provide supportive evidence for clinicians who are unable to enroll their patients in current clinical trials but consider TKI discontinuation a potentially beneficial strategy, particularly for reducing treatment-related toxicity, without compromising disease control in CML.
Conflict of Interest
The authors declare no potential conflicts of interest with respect to the research, authorship, and/or publication of this article. Informed consent was obtained for this publication.
Cite this article
Airosa Pardal A, Costa V. Dasatinib discontinuation and successful long term treatment free remission in chronic myeloid leukaemia paediatric patient – case report. Clin Oncol J. 2026;7(2):1–3.
Keywords
Chronic myeloid leukaemia; Paediatric; Treatment free remission
Copyright
© 2026 Vitor Costa. This is an open access article distributed under the terms of the Creative Commons Attribution 4.0 International License (CC BY-4.0).
